

Longitudinal patient data is health information about the same patient collected repeatedly over time and across care settings — visits, diagnoses, lab results, medications, imaging, procedures and outcomes — organized into one timeline. Because it shows how a patient’s health changes rather than a single snapshot, it is the foundation for chronic disease management, real-world evidence studies and modern healthcare AI models that predict what happens next.
Key takeaways
- Longitudinal patient data links many encounters for one person into a time-ordered record; a single visit or survey is cross-sectional.
- Common sources are EHRs and clinical notes, claims, lab and pharmacy data, imaging, registries and patient-generated data — often linked together.
- Building it depends on patient matching, standards such as HL7 FHIR and the OMOP Common Data Model, and HIPAA-compliant de-identification.
- For AI, longitudinal records power disease-progression and risk models and EHR foundation models; benchmark datasets such as EHRSHOT exist because single-visit data cannot test these tasks.
- The main risks are missing data, fragmentation, linkage errors and bias — all of which a data provider should be able to document.
What Is Longitudinal Patient Data?
Definition and a simple patient timeline

The same idea sits inside the definition of an electronic health record: an EHR is a digital record of a patient’s health information built up over time, from one or more visits and across care settings.
A simplified, illustrative patient timeline looks like this:
Types of Longitudinal Patient Data
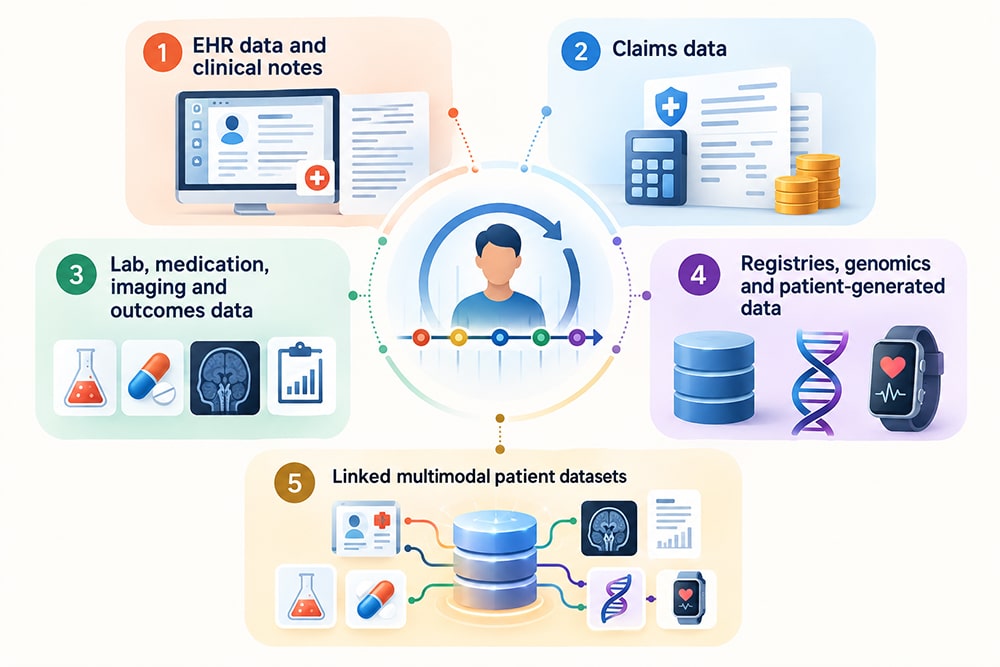
EHR data and clinical notes
EHRs hold structured fields (diagnoses, problem lists, vitals, orders, medications, lab results) and unstructured text (progress notes, discharge summaries, radiology and pathology reports). Adoption is close to universal in U.S. hospitals: ONC reports that as of 2024 more than 99% of non-federal acute care hospitals had adopted a certified EHR (HealthIT.gov). A large share of clinically important detail lives in free text, which is why clinical NLP and annotation are needed to make notes usable.
Claims data
Medical and pharmacy claims record billed services, diagnosis and procedure codes, dispensed drugs and costs. Claims exist to support payment, while EHR data is generated for clinical care. Claims follow a patient across providers within a payer, but carry little clinical detail.
Lab, medication, imaging and outcomes data
- Lab data: repeated results (HbA1c, eGFR, lipids, tumor markers) show how a disease is trending.
- Medication data: prescriptions, pharmacy fills and refill gaps show adherence, switching and treatment response.
- Imaging: serial scans with reports track progression or response (for example, tumor size over time).
- Outcomes: hospitalizations, readmissions, complications and mortality close the loop on what happened.
Registries, genomics and patient-generated data
Disease registries follow defined cohorts over time. Genomic and pathology data add molecular context, and wearables or patient-reported outcomes add between-visit data.
Linked multimodal patient datasets
The most valuable datasets link several of these sources for the same (de-identified) patient. The trade-offs look like this:
How Longitudinal Patient Data Works
Connecting records across encounters (patient matching and linkage)
A patient’s records are spread across hospitals, clinics, labs, pharmacies and payers, each with its own identifiers. Linking them is harder than it sounds: Pew cites ONC-contracted research that “found match rates as low as 50 percent even between organizations that share the same EHR vendor” (Pew Charitable Trusts, 2018).
Common linkage methods:
- Deterministic matching — links records on exact identifiers. Precise, but misses typos, name changes and new addresses.
- Probabilistic matching — scores similarity across fields such as name, date of birth and address to catch variants.
- Privacy-preserving record linkage (tokenization) — converts identifiers into encrypted tokens so de-identified datasets from different sources can be linked without exposing personal information.
Standardizing the data
Linked data is only useful if it speaks a common language:
- HL7 FHIR — HL7’s standard for exchanging healthcare data between systems.
- USCDI — the U.S. Core Data for Interoperability, ONC’s standardized set of health data classes and elements for nationwide exchange.
- OMOP Common Data Model — an open OHDSI standard that harmonizes the structure and content of observational data so the same analysis can run across many databases.
- Clinical code systems such as ICD-10 (diagnoses), CPT/HCPCS (procedures), LOINC (labs), RxNorm/NDC (drugs) and SNOMED CT (clinical terms).
Interoperability is improving but still incomplete, so many hospitals cannot yet send, receive, find and integrate outside records in every case.
De-identifying the data
For secondary use in the U.S., HIPAA’s Privacy Rule provides two de-identification methods: Expert Determination by a qualified expert, or Safe Harbor removal of 18 specified identifiers, including all elements of dates except the year (HHS). Dates matter for longitudinal data because the intervals between events carry the clinical meaning, so the de-identification method has to be chosen with the patient timeline in mind.
Organizing events along a patient timeline
Once matched, standardized and de-identified, each event is stamped with a (shifted) date and ordered per patient: encounter → diagnosis → order → result → medication → outcome. This timeline is the unit that analysts and AI models consume.
Longitudinal Patient Journey Examples
The examples below are illustrative patient journeys, not real patients.
Diabetes patient journey

A person with type 2 diabetes generates a classic longitudinal record: repeated glycemic measures such as HbA1c, medication starts and changes, kidney and eye screening, and complications. Because glycemic status is reassessed regularly, a diabetes record builds a natural time series. Over several years, those repeat values, prescriptions and outcomes show how each patient’s condition is changing.
Oncology treatment and outcomes
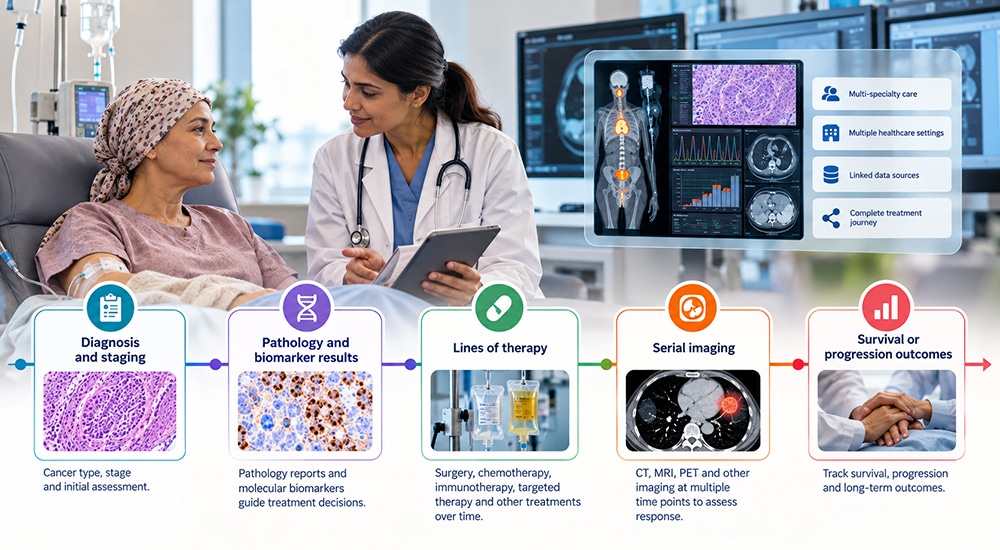
A cancer journey links diagnosis and staging, pathology and biomarker results, lines of therapy, serial imaging and survival or progression outcomes. Cancer care usually involves several specialties and settings, so the full treatment sequence is only visible when those sources are linked.
Medication response over time
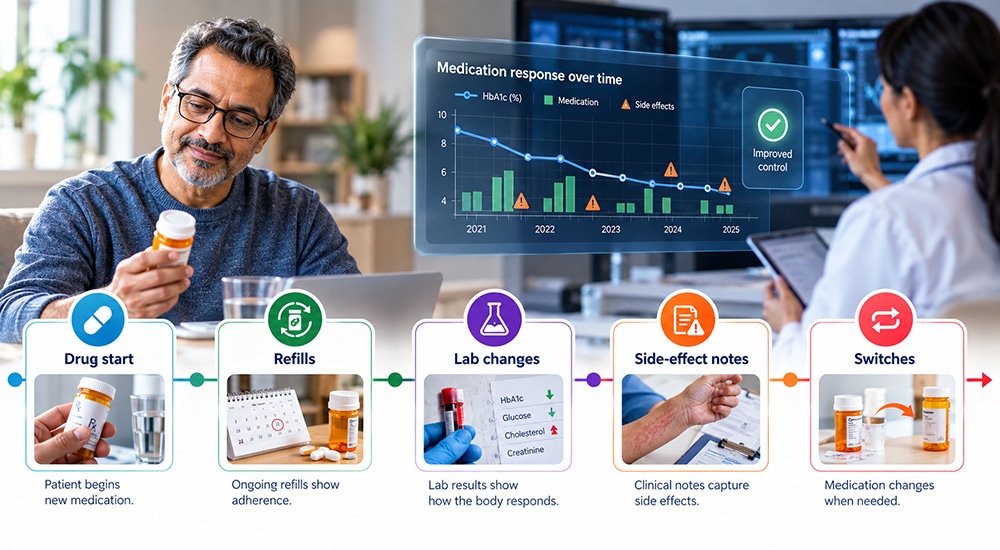
Following a drug start through refills, lab changes, side-effect notes and switches shows real-world effectiveness and adherence. The FDA calls this kind of routinely collected information real-world data (RWD), and the clinical evidence drawn from analyzing it real-world evidence (RWE).
Why Longitudinal Patient Data Matters for Research and Clinical Trials
- Real-world evidence: FDA’s Real-World Evidence Program, created under the 21st Century Cures Act, considers how real-world data can support regulatory decisions.
- Trial design and feasibility: historical patient journeys help estimate how many eligible patients exist and how fast outcomes occur.
- External comparators and long-term follow-up: longitudinal records can extend observation beyond a trial’s end date.
- Safety monitoring: sequences of exposure → event are the basis of pharmacovigilance.
- Care quality: clinicians can trend labs and vitals across visits instead of reviewing each encounter in isolation.
Longitudinal Patient Data for AI Training
Predictive models and disease progression
Time-ordered EHR data is what lets models forecast. In one widely cited study, Google and academic partners trained deep learning models on 46,864,534,945 EHR data points from 216,221 hospitalizations (114,003 patients), predicting in-hospital mortality, 30-day unplanned readmission, prolonged length of stay and discharge diagnoses; mortality prediction reached an AUROC of 0.93–0.95 across two hospitals (Rajkomar et al., npj Digital Medicine, 2018).
EHR foundation models
Newer models pretrain on entire patient timelines, much as language models pretrain on text:
- Med-BERT adapts the BERT architecture to structured EHR data, pretraining on large volumes of coded diagnoses across patient visits.
- Foresight is a generative transformer trained on hospital patient timelines in the UK and on MIMIC-III to forecast future disorders.
Medical LLMs and clinical NLP
Clinical notes are the narrative layer of the longitudinal record. Medical LLMs and NLP pipelines extract problems, medications, timelines and outcomes from that text — and need annotated, de-identified notes across many visits to learn how a patient’s story evolves.







